

Dry eye: why it occurs and when you should seek advice
One of the most frequent causes of ocular discomfort, and one that improves significantly with the right treatment.
What is dry eye?
Dry eye, also known as dry eye syndrome or ocular dryness, is a multifactorial disease of the ocular surface that occurs when the balance of the tear film and the eye surface is disrupted. This may be due to insufficient tear production, excessive evaporation or other factors that cause instability, inflammation, damage to the ocular surface or alterations in sensitivity.
The result is a poorly protected ocular surface that becomes inflamed and causes discomfort.
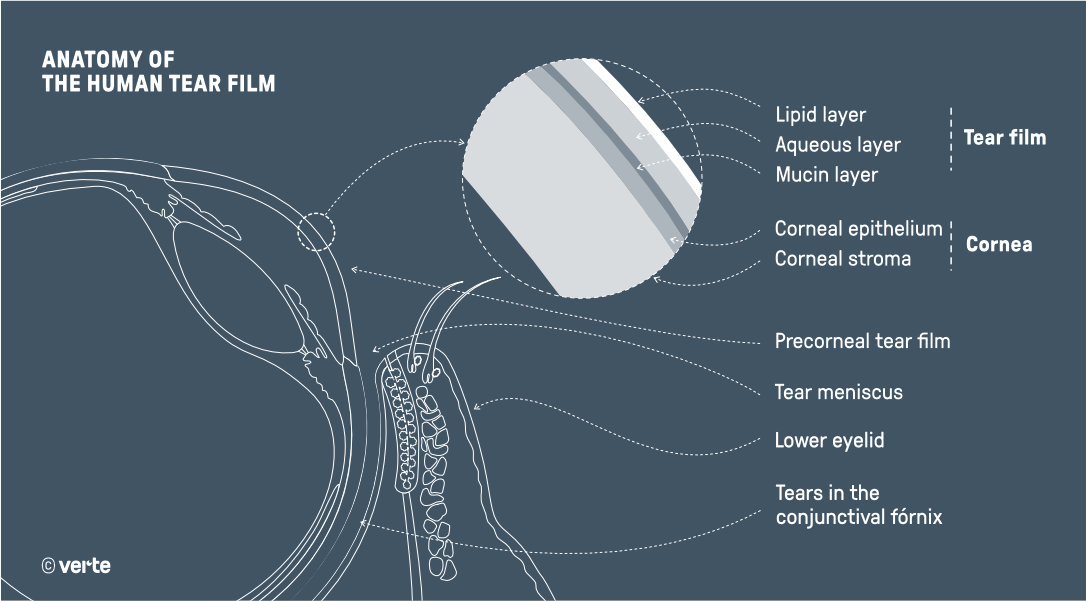
Tears are not just water: they are a multi-layered film that nourishes, protects and keeps the cornea transparent.
This tear film contains lipid, aqueous and mucin components that maintain the lubrication and protection of the entire ocular surface and the optical quality of the cornea.
When this balance is disrupted, the eye is left unprotected against the environment, screens or the passing of time, and the characteristic symptoms appear.
It is one of the most frequent ocular conditions, especially from the age of 50 onwards and in women during and after the menopause, although it is increasingly affecting younger people due to intensive screen use.
Symptoms of dry eye
Dry eye manifests with a combination of symptoms that tend to worsen throughout the day or in certain environments.
The most frequent symptoms are:
- A sensation of grittiness or a foreign body, as if there were something inside the eye
- Stinging, burning or itching
- Ocular redness
- Eye strain, especially when reading or using screens
- Sensitivity to light (photophobia)
- Intermittent blurred vision that improves with blinking
- Difficulty or discomfort when using contact lenses
One symptom that surprises many patients is excessive tearing.
Although it may seem contradictory, dry eye can trigger reflex tearing as a defensive response.
However, these tears are very watery and do not adequately restore the stability of the tear film.
For this reason, having watery eyes does not rule out dry eye disease.
Symptoms tend to worsen in dry environments, with air conditioning or heating, in windy conditions, in spaces with low humidity, and when we fix our gaze and blink less than normal, such as when looking at a phone or computer.
What are the causes of ocular dryness?
Ocular dryness is a multifactorial disease: it rarely has a single cause, but tends to develop through a combination of factors that reduce the quantity of tears or worsen their quality. Understanding what causes dry eye is the first step to treating it effectively, because treatment changes depending on the predominant factor in each person.
The most frequent causes and risk factors of ocular dryness are:
- Age. Tear production naturally decreases with age, which is why ocular dryness is particularly common from the age of 50 onwards.
- Hormonal changes. These mainly affect women during the menopause, pregnancy or through the use of contraceptives, one of the reasons why dry eye is more common in women.
- Prolonged screen use. When concentrating on a phone or computer, we blink far less, which promotes tear evaporation. This is known as computer vision syndrome.
- Environmental factors. Air conditioning, heating, wind and dry or polluted environments dry out the surface of the eye and aggravate ocular dryness.
- The use of contact lenses, which alter the stability of the tear film.
- Certain medications. Antihistamines, antidepressants, anxiolytics and some antihypertensives, among others, can reduce tear production.
- Systemic diseases. Autoimmune diseases such as Sjögren's syndrome, rheumatoid arthritis or lupus, as well as thyroid disorders and diabetes.
- Previous eye surgery and eyelid conditions such as blepharitis, which affects the glands that produce the lipid layer of the tear film.
It is common for several of these factors to coincide in the same person, which explains why ocular dryness is one of the most widespread ocular conditions. Identifying which factors predominate in each case is precisely what enables a personalised treatment plan to be designed.
Types of dry eye
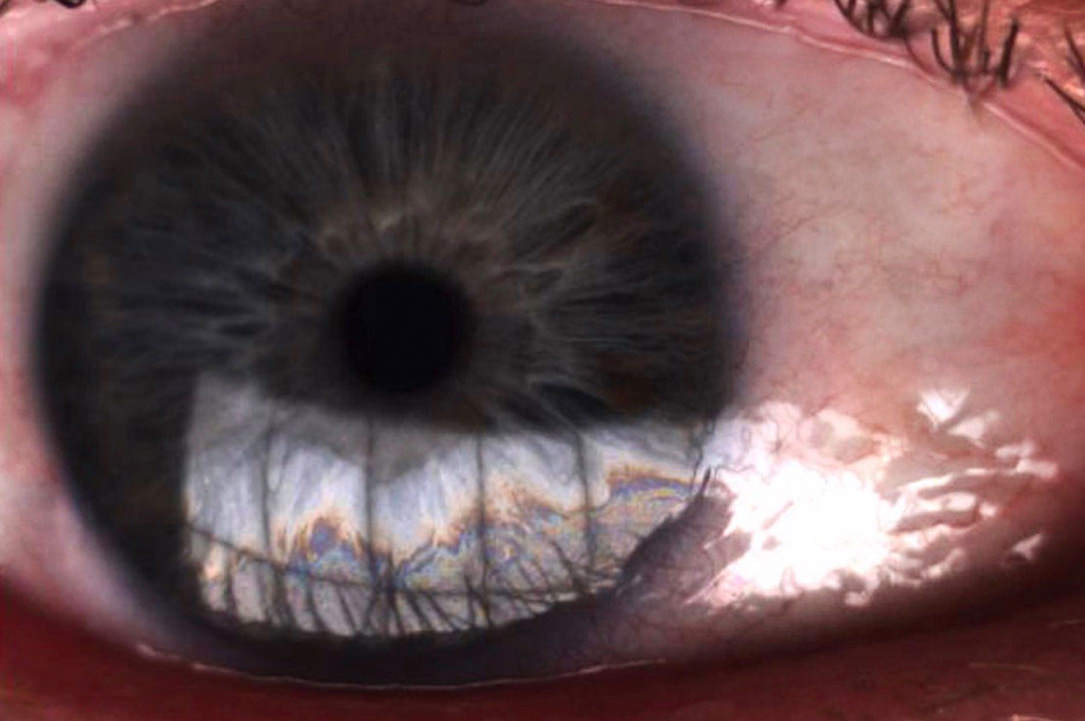
To understand dry eye, it is important to know the tear film, which is made up of three layers: an outer lipid (fatty) layer produced by the Meibomian glands of the eyelids, a middle aqueous layer produced by the lacrimal glands, and an inner mucin layer that helps tears adhere to the surface of the eye. Depending on which layer fails, three main types are distinguished:
- Evaporative dry eye. This is the most common type. The quantity of tears may be normal, but they evaporate too quickly because the lipid layer fails, usually due to Meibomian gland dysfunction (often related to blepharitis).
- Aqueous-deficient dry eye. The eye does not produce a sufficient quantity of tears. This is the type most associated with autoimmune diseases such as Sjögren's syndrome.
- Mixed dry eye. This combines a production deficit and excessive evaporation. It is very common, and in these cases many patients simultaneously present reduced production and excessive evaporation. Inflammation and damage to the ocular surface can contribute to both mechanisms being maintained or worsening.
Identifying the type of dry eye is essential, because the treatment differs in each case.
When should you consult an ophthalmologist?
Mild and occasional dry eye discomfort can be relieved with simple measures. However, you should consult an ophthalmologist when:
- Symptoms are persistent, recur frequently or worsen over time
- You notice blurred vision that does not fully correct itself
- You experience ocular pain, not just discomfort
- Redness is constant
- The artificial tears you use on your own are no longer providing relief
- You wear contact lenses and are increasingly unable to tolerate them
Dry eye that persists over time without treatment is not just a matter of discomfort: it can damage the surface of the cornea and lead to complications such as keratitis, a corneal inflammation that requires medical attention.
Furthermore, if intense pain, photophobia (discomfort with light), decreased vision, intense redness in one eye, or pain and redness while wearing contact lenses appear, a priority ophthalmological assessment should be requested. These signs may be due to other eye diseases and should not automatically be attributed to dry eye.
For all these reasons, professional diagnosis is very important.
How is dry eye diagnosed?
The diagnosis of dry eye goes beyond listening to symptoms. In a complete ophthalmological assessment, the quantity and quality of tears are studied, along with the state of the ocular surface and the functioning of the glands that produce each layer of the tear film. This makes it possible to determine not only whether dry eye is present, but what type and degree of severity, from mild to severe dry eye.
The most common tests include evaluation of the tear film, measurement of the time it takes for tears to evaporate, study of the Meibomian glands and assessment of damage to the ocular surface using staining. Some instruments (such as the Keratograph) analyse tears from many perspectives and provide a very useful report for informing you graphically, evaluating the initial state and the response to treatment. This detailed study is what enables us to design a personalised and effective treatment plan.
Is there a treatment for dry eye?
Dry eye is a chronic condition that, as of today, has no definitive cure, but can be very effectively controlled with the right treatment. The aim is twofold: to relieve symptoms and protect the ocular surface to prevent complications.
Treatment depends on the type and severity of each case, and ranges from hygiene measures and lifestyle changes to specific in-clinic treatments. The important thing to understand is that not all dry eyes are the same, and that the key lies in treating the specific cause for each patient, not just relieving dryness on a temporary basis.